
Physical Therapy Billing Units Explained – The 8-Minute Rule & Beyond

Treating patients requires intense focus and clinical expertise. You spend your day analyzing movement patterns, manipulating joints, and guiding patients through recovery exercises. However, if your clinic fails to track treatment time accurately, you will lose a massive amount of hard-earned revenue. Insurance companies scrutinize rehabilitative claims closely. They demand precise time tracking before paying for your hands-on care. Mastering physical therapy billing units protects your bottom line. You must understand exactly how Medicare and private insurers calculate time based on the strict 8-Minute Rule. Submitting a claim with the wrong unit count triggers an instant denial. This guide breaks down everything you need to know about time-based billing. We explain the difference between specific code types, outline the exact time thresholds, and show you how to calculate your daily units flawlessly. The Difference Between Timed and Untimed Codes Before you can calculate any math, you must classify your treatments correctly. The American Medical Association separates physical therapy procedures into two distinct categories. Understanding this separation is the foundation of physical therapy medical billing. Untimed Codes Untimed codes represent a flat service fee. You bill these codes exactly once per session, regardless of how long the procedure actually takes. Whether an evaluation takes 20 minutes or 45 minutes, the insurance company pays the exact same flat rate. Common untimed codes include: 97161 to 97163: Physical therapy evaluations. 97164: Patient re-evaluations. 97010: Hot or cold pack application. 97022: Whirlpool therapy. Note: You cannot add the minutes spent on untimed codes into your daily 8-Minute Rule calculations. You must keep this time completely separate from your hands-on therapy minutes. Timed Codes Timed codes apply to direct, one-on-one patient care. These codes require constant attendance from the physical therapist or assistant. You bill these services in 15-minute increments based on the total time spent actively treating the patient. Common timed codes include: 97110: Therapeutic exercises to develop strength and endurance. 97140: Manual therapy techniques like joint mobilization. 97112: Neuromuscular re-education for balance and coordination. 97530: Therapeutic activities to improve functional performance. Mastering the Medicare 8-Minute Rule Insurance companies need a standardized way to pay for time-based care. Medicare created the 8-Minute Rule in the year 2000 to regulate physical therapy billing units. This rule dictates exactly how many units you can charge based on the total minutes of direct treatment you provide. The rule states that you must provide at least 8 minutes of direct, one-on-one treatment to bill for a single unit of service. If you provide 7 minutes of manual therapy and stop, you cannot bill a unit for that specific service unless you combine it with another timed code. As your treatment time increases, you unlock the ability to bill multiple units. You reach a new billing unit every 15 minutes after passing the initial 8-minute threshold. The Official Time Thresholds Keep this exact chart at your front desk. You will use these thresholds every single day to verify your claims before submission. Total Treatment Time Billable Units Allowed 8 to 22 minutes 1 Unit 23 to 37 minutes 2 Units 38 to 52 minutes 3 Units 53 to 67 minutes 4 Units 68 to 82 minutes 5 Units 83 to 97 minutes 6 Units How to Calculate Total Units Effectively Figuring out your total units requires a simple mathematical formula. You must look at the entire treatment session as a whole rather than viewing each exercise in isolation. Follow this step-by-step process to calculate your units correctly: Isolate the Timed Care: Exclude any time spent on evaluations or untimed modalities like ice packs. Add the Minutes: Add the total minutes of all timed, one-on-one services together. Divide by 15: Divide your total combined minutes by 15 to find your base units. Check the Remainder: Look at the leftover minutes. If the leftover time is 8 minutes or greater, you add one more billing unit to your total. If the remainder is 7 minutes or less, you drop the extra time and cannot bill for it. Handling Mixed Remainders and Multiple Codes Calculating units gets slightly complicated when you perform multiple different therapies during the same visit. You must split the total allowed units across the different CPT codes fairly. Medicare requires you to assign the units based on which service actually took the most time. A Practical Clinical Scenario Imagine you treat a patient for a total of 40 minutes. You spend 24 minutes on therapeutic exercises (97110). You spend 16 minutes on manual therapy (97140). First, you look at your total time. According to the 8-Minute Rule chart, 40 total minutes allows you to bill exactly 3 units. Now, you must distribute those 3 units. You look at the individual times. You spent 24 minutes on therapeutic exercise. Divided by 15, this equals 1 base unit with a remainder of 9 minutes. Because the remainder is greater than 8, you bill 2 units for therapeutic exercise. You spent 16 minutes on manual therapy. This equals 1 base unit with a remainder of 1 minute. You drop the 1 minute and bill 1 unit for manual therapy. Adding them together, you have 2 units of 97110 and 1 unit of 97140. This matches your maximum allowed total of 3 units perfectly. The Single Service Minimum Rule Therapists often wonder what happens to very short treatments. Sometimes you only spend 5 or 6 minutes on a specific intervention. The rules for billing these short sessions are incredibly strict. If a single timed service lasts less than 8 minutes, you absolutely cannot bill it by itself. However, you do not always lose this time. You can combine those short minutes with another timed service provided on the same day. For example, you spend 5 minutes on manual therapy (97140) and 10 minutes on therapeutic activities (97530). Neither service meets the 15-minute mark for a full standard unit. However, combined, they equal 15 total minutes. According to the rule, 15 total minutes equals 1 billable unit. Because therapeutic activities (10 minutes)
Incident-to Billing: Requirements, Rules, and Common Mistakes

Incident-to billing is a Medicare provision that allows a non-physician practitioner, such as a nurse practitioner or physician assistant, to bill a service under a supervising physician’s National Provider Identifier at 100% of the Medicare physician fee schedule, rather than the standard 85% rate paid when the NPP bills under their own NPI. To qualify, every requirement has to be met at the same time during the encounter: the physician must have performed the initial evaluation and established the plan of care, the service must be part of that ongoing plan for an existing problem, the physician must be directly and physically available onsite, and the visit must take place in a non-institutional outpatient setting. Practices navigating this level of complexity often rely on expert medical billing services to keep incident-to claims compliant and properly reimbursed. Because all of these conditions have to apply simultaneously, incident-to billing is one of the more compliance-sensitive areas in Medicare billing, and it’s also one of the most frequently misapplied. This is one of the reasons many practices turn to expert medical billing services rather than managing incident-to compliance entirely in-house. What Is Incident-to Billing? Incident-to billing lets a practice bill an NPP’s service as if the supervising physician performed it, which results in reimbursement at the full physician fee schedule rate instead of the reduced rate that applies when an NPP bills independently under their own NPI. The Centers for Medicare & Medicaid Services (CMS) defines the coverage criteria for incident-to services and supplies directly, and this is a Medicare-specific provision, not a universal billing concept, even though the underlying logic of physician-supervised care shows up in other contexts. Under incident-to billing, the NPP is not identified to the patient or the payer on the claim. Only the supervising physician is credited for the service on the bill itself, even though the NPP performed the visit. Core Requirements for Incident-to Billing All of the following conditions have to be met at the same time for a service to qualify as incident-to. Missing any single one disqualifies the claim from incident-to billing, regardless of how well the others are satisfied. Initial physician visit. The supervising physician must have personally performed the first evaluation of the specific condition being treated and established the original plan of care. Established plan of care. The service being billed has to be part of an ongoing, active treatment plan for an existing problem, not a new evaluation. Direct supervision. The supervising physician must be physically present in the same office suite and immediately available to assist if needed, though not necessarily in the exam room itself. Non-institutional setting. The visit must occur in a non-facility outpatient setting, such as a private office (Place of Service 11), rather than a hospital, emergency department, or skilled nursing facility. Same practice or employer. The NPP must be an employee, leased employee, or contractor of the same physician or group practice as the supervising physician. Where Incident-to Billing Does Not Apply Several situations are explicitly excluded from incident-to billing, and treating any of them as an exception is one of the most common compliance risks in this area. New patients. Incident-to billing cannot be used for a patient who is new to the practice, since there is no established plan of care yet for the physician to build on. New problems. If an established patient presents with a new symptom or a distinct, previously unevaluated condition, the physician has to personally evaluate that new issue and update the plan of care before any related follow-up visits can be billed incident-to. Facility settings. Incident-to billing does not apply in hospitals, emergency departments, or skilled nursing facilities, regardless of how closely the physician is supervising. Most commercial payers. Incident-to billing rules apply specifically to Medicare. Many commercial insurance plans do not recognize incident-to billing at all and require the NPP to bill directly under their own NPI instead. Incident-to vs. Split/Shared Billing Incident-to billing is sometimes confused with split, or shared, billing, but they are distinct concepts with different requirements. Incident-to billing applies to an NPP’s visit for an established problem under a physician-established plan of care, billed entirely under the physician’s NPI. Split, or shared, billing typically applies when a physician and an NPP each perform a substantive portion of the same visit, and the billing determination depends on which provider performed the substantive portion of the encounter, following separate CMS guidance from incident-to rules. Understanding where each of these fits among the broader types of billing in healthcare helps prevent the two from being treated as interchangeable. Treating the two as interchangeable, or applying incident-to logic to a scenario that’s actually a split/shared visit, is a documentation and compliance risk worth addressing directly with billing staff. Common Mistakes in Incident-to Billing Negligent supervision. Assuming that being reachable by phone or text while off-site satisfies the direct supervision requirement. The physician has to be physically present in the office suite, not just contactable. Billing a new complaint under an old plan. Continuing to bill incident-to when an established patient raises a new medical issue that hasn’t yet been evaluated by the physician. Wrong location. Attempting to apply incident-to billing to services performed in a hospital-owned or institutional outpatient space, where the setting requirement automatically disqualifies it. Vague documentation. Failing to clearly document the physician’s active participation, ongoing oversight, and physical availability during the visit, which leaves the claim unsupported if it’s ever reviewed. Applying it to commercial payers by default. Assuming a commercial insurer follows the same incident-to rules as Medicare without confirming that payer’s specific policy first. Documentation That Supports Compliant Incident-to Billing Strong documentation is what separates a defensible incident-to claim from one that creates audit exposure. Since most of this documentation now lives inside an EMR, staff who complete a structured EMR training guide are typically better positioned to capture it correctly the first time. At minimum, the chart should clearly show: The date and content of the physician’s initial
Chiropractic Billing Cheat Sheet – Codes, Modifiers & Documentation Tips

Running a profitable chiropractic clinic requires a sharp eye for detail. Your main focus is helping patients recover from pain and regain their mobility. However, if your medical billing process falls apart, your practice will struggle to survive. Insurance companies reject claims for the smallest errors. A missing modifier or a mismatched diagnosis code will stop a payment instantly. To keep your revenue cycle healthy, your staff needs a reliable system to submit perfectly clean claims every single time. This complete chiropractic billing cheat sheet gives you the exact tools you need. Accurate chiropractic billing relies on matching specific Current Procedural Terminology codes for spinal manipulation with precise diagnosis codes. You must also apply mandatory modifiers and prove medical necessity through excellent daily documentation. We will break down the exact codes you use every day, explain how to navigate Medicare requirements, and show you how to document your notes to survive any insurance audit. The Core Chiropractic CPT Codes The foundation of your billing system revolves around procedure codes. These codes tell the insurance company exactly what physical service you provided during the patient visit. Unlike general medical practices that use hundreds of different procedure codes, chiropractors rely heavily on a small, highly specific set of numbers. Chiropractic Manipulative Treatment Codes Chiropractic Manipulative Treatment codes describe your physical spinal adjustments. The American Medical Association bases these codes on the total number of body regions you treat during a single session, not the number of individual thrusts you perform. The human spine is divided into five specific billing regions. These regions are the cervical, thoracic, lumbar, sacral, and pelvic areas. You must select the code that matches the exact number of regions you adjust. Here is a quick reference table for your daily manipulation codes: CPT Code Description Treatment Scope 98940 Spinal manipulation, 1 to 2 regions Commonly used for localized neck or low back pain. 98941 Spinal manipulation, 3 to 4 regions The most frequently billed code for widespread spinal issues. 98942 Spinal manipulation, 5 regions Used for full spine adjustments across all five regions. 98943 Extraspinal manipulation Used for adjusting extremities like shoulders, wrists, or knees. Evaluation, Management, and Therapy Codes Chiropractors provide more than just joint adjustments. You also evaluate new injuries and guide patients through physical rehabilitation. You must report these extra services accurately to receive proper payment. Your front desk should memorize these essential evaluation and therapy codes: 99202 through 99205: These codes cover new patient office visits. You choose the specific number based on the complexity of your initial exam. 99212 through 99215: These codes apply to established patients who require a new evaluation for a completely new injury. 97110: This code covers therapeutic exercises. You bill this when you teach a patient specific movements to develop strength, range of motion, and endurance. 97140: This code describes manual therapy techniques. It includes joint mobilization and manual lymphatic drainage performed outside of the standard spinal adjustment. Mastering Modifiers in Chiropractic Billing Sometimes, a basic procedure code does not tell the whole story. You need a way to give the insurance company extra context about the visit. Modifiers are special two-character codes you attach to your main procedure code. If you forget to add a required modifier, the insurance company will deny your claim immediately. The Mandatory Medicare AT Modifier When dealing with Medicare patients, the AT modifier is absolutely critical. Medicare only covers active, corrective treatment for spinal subluxations. They strictly refuse to pay for routine maintenance care. The AT modifier stands for “Active Treatment.” Appending this modifier to your 98940, 98941, or 98942 code tells Medicare that you are actively fixing a specific problem. If a patient reaches maximum medical improvement and you continue to treat them just to maintain their comfort, you cannot use the AT modifier. Without the AT modifier, Medicare automatically treats the claim as maintenance care and denies the payment. Breaking Bundles with Modifiers 59 and XS Insurance computer systems automatically bundle certain services together. If you bill a spinal adjustment (98940) and manual therapy (97140) on the exact same day, the system assumes the therapy was just a normal part of the adjustment. The insurance company will only pay you for the adjustment. To get paid for both services, you must prove they were distinct and separate. Historically, billers used Modifier 59 to indicate a distinct procedural service. You would attach Modifier 59 to the manual therapy code to stop the system from bundling the payments. Today, many insurance companies prefer more specific X-set modifiers. The most common replacement is the XS modifier. The XS modifier tells the payer that the manual therapy occurred on a completely separate anatomical structure than the spinal adjustment. For example, if you adjust the cervical spine but perform manual therapy on a swollen knee, you attach the XS modifier to your therapy code. Pairing CPT Codes with Accurate ICD-10 Diagnoses Your procedure code explains what you did, but your diagnosis code explains why you did it. The International Classification of Diseases (ICD-10) manual contains thousands of diagnosis codes. You must pair your physical treatments with the correct diagnosis to prove medical necessity. Avoiding Geographic Mismatches Much like the strict rules found in podiatry CPT codes and modifiers, chiropractic billing demands precise anatomical mapping. You cannot treat a patient’s neck and link that treatment to a lower back diagnosis. This error is called a geographic mismatch. If you bill CPT 98940 for a cervical adjustment, your diagnosis code must describe a problem in the cervical region. If you link a cervical adjustment to ICD-10 code M54.50 (low back pain), the payer will reject the claim instantly. Common Chiropractic Diagnosis Codes Your clinical notes should clearly identify the specific subluxation or pain point. Using highly specific codes prevents unnecessary audits. Review this list of common diagnosis codes used in daily practice: M99.01: Segmental and somatic dysfunction of the cervical region. M99.02: Segmental and somatic dysfunction of the thoracic region. M99.03: Segmental and somatic dysfunction of
How Much Do Medical Coders Make? Salary Breakdown by Experience and Region

Medical coder salaries in the United States generally fall in a broad range depending on which source is measuring, with AAPC’s salary survey data for certified coding professionals typically landing higher than the U.S. Bureau of Labor Statistics’ broader occupational wage data, which covers a wider category of medical records roles. In Canada, hourly wages for health information management coders range roughly from $22.00 to $46.19 per hour according to the Government of Canada’s Job Bank, with meaningful variation by province and experience level. Across both countries, certification, years of experience, and specialization are the three factors that move an individual coder’s pay the most. Practices looking to build a well-compensated, well-trained coding function often pair that hiring strategy with professional medical billing services to keep both accuracy and cost under control. This guide breaks down what drives that range, what to expect at different career stages, and why salary figures you’ll find online can look so different depending on where you look. For practices weighing whether to build an in-house team or outsource entirely, professional medical billing services can offer a useful point of comparison against in-house coder salary costs. Why Medical Coder Salary Figures Vary So Much Before looking at specific numbers, it’s worth understanding why coder salary data varies as much as it does across different sources. This variation often mirrors the same complexity found across different types of billing in healthcare, since compensation frequently scales with how specialized a coder’s billing work becomes. Survey population differences. AAPC’s salary surveys specifically measure certified medical coding professionals, typically its own membership base, while the U.S. Bureau of Labor Statistics tracks a broader occupational category that includes a wider range of medical records and health information roles, some of which pay less than coding-specific positions. Certification status. Certified coders consistently report higher average earnings than non-certified coders performing similar work, which is one of the most reliable patterns across salary data. Aggregator site methodology. Sites like Glassdoor, Indeed, and ZipRecruiter pull from a mix of self-reported and modeled salary data that updates frequently and can vary significantly from month to month, even for the same job title and location. Regional cost of living. Both US and Canadian salary data show substantial regional variation, driven partly by cost of living and partly by regional healthcare industry concentration. Given these differences, it’s more useful to think in terms of a realistic range for your specific situation than to anchor on any single number. This is especially relevant for compensation tied to specific claim types, such as those explained in this incident-to billing rules guide, since specialized billing knowledge often affects a coder’s earning potential. US Salary by Experience Level AAPC’s salary survey data breaks compensation down by career stage, and the pattern is consistent even as exact figures shift from year to year: coder pay increases substantially with experience. Career Stage Years of Experience Typical Responsibilities Entry-Level 0–1 years Claims submission, tracking basic outpatient files, clearing simple insurance rejections Mid-Career 2–9 years Complex surgical coding, primary reimbursement review, denial management Senior Level 10–15 years Auditing practice documentation, regulatory compliance monitoring, revenue cycle oversight Late Career 31+ years Managing enterprise coding teams, compliance training, directing health informatics According to AAPC’s salary survey reporting, entry-level coders in the US have generally started somewhere in the low-to-mid $40,000s annually, with average compensation across the full certified coder population reported in different recent surveys in the high $50,000s to mid $60,000s range, and late-career professionals with several decades of experience reporting notably higher average compensation. Because AAPC’s own reported figures have varied somewhat between recent survey years, treat these as directional bands rather than a single fixed number for your specific situation. The Certification Pay Premium One of the most consistent patterns in coder compensation data is the gap between certified and non-certified coders. AAPC’s reporting has repeatedly shown certified coders earning meaningfully more on average than coders without a recognized credential performing similar work, and entering the field without certification has been associated with a lower starting wage tier compared to entering with a credential like the Certified Professional Coder (CPC) already in hand. Advanced specialization credentials, such as those focused on auditing or compliance, have been associated with further increases in reported average compensation beyond the standard CPC baseline. Coders weighing which additional credential to pursue next sometimes ask is EMR certification worth it, since electronic records fluency is increasingly tied to coding and documentation accuracy. US Regional Salary Variation Geographic location is one of the largest drivers of coder salary variation within the United States. AAPC’s regional survey breakdowns have generally shown: Higher-paying regions, such as the Pacific region (including California, Alaska, and Hawaii) and Mid-Atlantic states (including New Jersey, New York, and Pennsylvania), tend to report average compensation well above the national figure, often tied to higher regional cost of living. Lower-paying regions, such as parts of the East South Central region (including Alabama, Kentucky, and Tennessee), have generally reported average compensation below the national figure, often tied to lower regional cost of living. State-level variation can be substantial even within the same broad region, so checking state-specific data is more useful than relying on a regional average alone when evaluating a specific opportunity. Medical Coder Salaries in Canada Canadian coder compensation is reported somewhat differently than in the US, both because of currency and because provincial healthcare administration creates its own regional variation. The Government of Canada’s Job Bank reports that health information management coders across Canada typically earn between $22.00 and $46.19 per hour, which converts to a wide annual range depending on hours worked and specific role. This is a broad national range, and specific provinces, including Ontario, tend to see figures within that range shift based on local demand and cost of living. Various private salary aggregator sites report differing annual averages for Ontario specifically, generally in the range of roughly $45,000 to $70,000 depending on the site and reporting period, which reflects the same aggregator
Physician Billing Explained: How Provider Claims Differ from Facility Billing

Physician billing covers the professional services a doctor or clinician personally provides, submitted on a CMS-1500 form using CPT and HCPCS codes to reflect the physician’s time, skill, and medical decision-making. Facility billing covers the hospital or clinic’s overhead, submitted on a UB-04 form using revenue codes and, for inpatient care, ICD-10-PCS codes to reflect room charges, equipment, supplies, and staff support. Many outpatient visits generate both types of claims at once, which is why a patient sometimes receives two separate bills for what felt like a single visit. Facilities looking to keep both claim types accurate and compliant often rely on our medical billing services to manage the process end to end. This guide breaks down exactly what separates these two claim types and why understanding the difference matters for both providers and patients trying to make sense of a billing statement. It’s also part of why many practices choose to outsource to our medical billing services rather than manage dual claim types internally. What Is Physician Billing? Physician billing, sometimes called professional billing, covers the services a specific clinician personally delivers: the exam, the diagnosis, the procedure performed, and the medical decision-making behind the care. These claims are submitted on the CMS-1500 form, whether electronically or on paper, and rely primarily on CPT codes for the procedures and services performed and HCPCS codes for supplies, equipment, and certain non-physician services. The professionals who translate this clinical work into codes play a specialized role, and compensation trends for that role are covered in this medical coder salary guide. Because physician billing reflects an individual clinician’s work, the claim is tied specifically to that provider’s National Provider Identifier (NPI) and credentials, not to the facility where the service happened to take place. Situations where a service is performed by clinical staff under a physician’s supervision fall under a distinct set of requirements, outlined in this incident-to billing rules guide. What Is Facility Billing? Facility billing, sometimes called institutional billing, covers the resources the hospital or clinic itself provides: the room, the equipment, medical supplies, and the nursing and support staff involved in the visit. These claims are submitted on the UB-04 form and rely on revenue codes to categorize departmental charges, along with ICD-10-PCS codes for inpatient procedures specifically. Facility billing reflects the overhead and infrastructure cost of delivering care, independent of which individual physician performed the service. This is just one of several distinct categories that fall under the broader types of billing in healthcare. Key Differences at a Glance Category Physician Billing Facility Billing Claim form CMS-1500 UB-04 Primary coding CPT and HCPCS codes Revenue codes; ICD-10-PCS for inpatient procedures What it reflects Physician time, skill, and medical decision-making Room charges, equipment, supplies, and staff support Tied to The individual provider’s NPI The facility itself Why Outpatient Visits Often Generate Two Separate Bills When a patient receives outpatient care at a hospital-affiliated clinic, the visit is frequently split into two components: one claim for the physician’s professional work and a separate claim for the facility’s overhead cost of hosting that visit. This is standard practice for hospital outpatient departments, and the two claims are structured to cover distinct cost components without overlapping, since the facility claim generally excludes the physician’s own work. This split-billing structure is the most common reason a patient is confused to see two separate charges, sometimes from two different billing entities, for what they experienced as one continuous visit. How Coding Differs Between Physician and Facility Claims The coding systems used for each claim type reflect what each claim is actually describing. Seeing how these codes are applied in real scenarios can make the distinction clearer, as shown in this medical coding examples guide. CPT and HCPCS codes (physician billing) describe the specific procedure, service, or supply the physician provided or ordered, down to a fairly granular level of clinical detail. Revenue codes (facility billing) categorize charges by hospital department or service line, such as radiology, pharmacy, or operating room time, without describing the specific clinical procedure at the same level of detail a CPT code would. ICD-10-PCS codes (facility billing, inpatient only) describe inpatient procedures specifically, and are distinct from the ICD-10-CM diagnosis codes used across both physician and facility claims to document the patient’s condition. Because these two claim types use different coding systems for different purposes, a coding or billing team working across both physician and facility claims needs fluency in both systems, not just one. Common Reasons Physician Claims Get Denied Physician claims tend to see a lower denial rate than facility claims overall, largely because they involve fewer service elements per claim, but they still carry their own common denial patterns. Strong documentation practices are often the deciding factor, which is covered in more detail in this guide on how billing notes prevent denials: Mismatched or missing modifiers on procedures billed alongside an E/M visit Incorrect place-of-service coding, particularly when a physician provides care in more than one setting, such as an office and a hospital outpatient department Medical necessity documentation gaps, where the diagnosis code doesn’t clearly support the procedure billed Provider credentialing issues, where the billing NPI isn’t properly enrolled or linked to the specific payer or facility How YTC Healthcare’s Team Handles This Physician billing and facility billing require different coding fluency, and a claim built with the wrong coding logic for its claim type is one of the more preventable sources of denial and delayed reimbursement. YTC Healthcare’s Medical Billing and Coding team codes physician claims specifically against CPT and HCPCS standards tied to the individual provider’s documented work, keeping that distinct from any facility-side revenue coding that may apply to the same visit. The Compliance and Reporting team verifies that provider credentialing and NPI enrollment are current with each payer before claims are submitted, since a credentialing gap can stall an otherwise correctly coded claim. When a physician claim is denied, the Denial Management and Appeals team identifies whether the issue is a
Chiropractic Billing Services – Common CPT Codes & Denial Triggers

Running a successful chiropractic practice requires more than just excellent patient care. It requires a healthy revenue cycle. Medical billing in the chiropractic field is highly specialized. Unlike general medical practices, chiropractors rely on a very specific set of procedure codes. When your staff submits a claim, insurance companies scrutinize every detail. A single missing modifier or an incorrect diagnosis code can stop a payment instantly. Mastering chiropractic billing services protects your clinic from financial loss. You need to know exactly how to code a spinal adjustment and when to report manual therapy separately. Furthermore, you must understand why insurance companies reject claims so you can stop these errors before they happen. This guide breaks down the most common billing codes you will use every day. We also explain the biggest denial triggers, including missing modifiers and medical necessity failures. By improving your coding accuracy, you keep your cash flow strong and focus your energy back on helping your patients heal. The Core of Chiropractic Medical Billing: CPT Codes Current Procedural Terminology (CPT) codes tell the insurance company exactly what physical service you provided to the patient. For a chiropractor, these codes generally fall into two distinct categories. The first category covers the actual physical adjustment of the spine or extremities. The second category covers the physical therapy and modalities used to support the adjustment. Every time you submit a claim, you must select the code that perfectly matches your clinical notes. If your notes say you adjusted the neck, but you bill a code for a full-spine adjustment, the insurance company will deny the claim or penalize you during a future audit. Chiropractic Manipulative Treatment (CMT) Codes Chiropractic Manipulative Treatment codes describe the core service of your practice. These codes are not based on how many individual adjustments you perform. Instead, they are based on how many distinct body regions you treat. The American Medical Association defines five spinal regions for billing purposes. These regions are the cervical spine, the thoracic spine, the lumbar spine, the sacral spine, and the pelvic region. Here are the specific codes you will use daily: 98940: You use this code for a spinal manipulation covering one to two regions. For example, if you only adjust the patient’s cervical and thoracic regions, you report 98940. 98941: You use this code for a spinal manipulation covering three to four regions. This is the most frequently billed code in the industry. An example is adjusting the cervical, thoracic, and lumbar spine during a single visit. 98942: You use this code when you adjust all five spinal regions. Your clinical documentation must clearly prove that every single region required treatment. 98943: You use this code for extra-spinal manipulation. This covers adjustments to areas outside the spine, such as the shoulders, wrists, knees, or ribs. Therapy and Modality Codes Chiropractors do much more than adjust the spine. You often provide manual therapy, prescribe exercises, and use mechanical tools to help muscles relax. Chiropractic medical billing requires you to report these supportive services accurately. 97140: This code covers manual therapy techniques. It includes myofascial release, joint mobilization, and manual lymphatic drainage. You bill this code in 15-minute increments. 97110: This code covers therapeutic exercises. You use this when you instruct a patient on specific exercises designed to develop strength, endurance, or flexibility. This is also billed in 15-minute increments. 97012: This code covers mechanical traction therapy. You use this when a specialized machine applies traction to the patient’s spine to relieve nerve pressure. Info: Medicare has very strict rules regarding therapy codes. While private insurers often pay for therapeutic exercises and manual therapy, Medicare typically only covers the actual spinal manipulation codes (98940, 98941, and 98942). Understanding Common Denial Triggers Knowing your CPT codes is only half the battle. Insurance companies actively look for reasons to reject claims. A rejected claim is called a denial. Denials cost your practice money and waste hours of administrative time. By understanding what triggers a denial, you can train your staff to submit clean claims on the very first try. The Danger of Bundling Issues Bundling is the most common reason for a rejected chiropractic claim. The National Correct Coding Initiative creates rules that bundle certain services together. The system assumes that if you perform two specific services on the same day, one service is just a natural part of the other. Therefore, the insurance company will only pay you for the main service. This creates a massive problem for chiropractors who use manual therapy (97140) and perform an adjustment (98940) on the same day. The billing system automatically bundles 97140 into the adjustment code. If you perform manual therapy on the exact same spinal region where you performed the adjustment, you cannot bill them separately. However, if you perform manual therapy on a completely different body part, you deserve to be paid for both services. To get paid, you must use a special billing modifier. Modifiers 59 and the X Modifiers A modifier is a two-character code you attach to your main CPT code. It tells the insurance company that a special circumstance applies to this visit. When you need to break a bundling rule legally, you use Modifier 59. Modifier 59 indicates that a procedure was a distinctly separate service from the main adjustment. For example, if you adjust the lumbar spine (98940) but perform 15 minutes of manual therapy (97140) on the patient’s knee, these are separate services. You would attach Modifier 59 to the 97140 code. This tells the computer system not to bundle the payment. Because providers abused Modifier 59 in the past, insurance companies created more specific options called X modifiers. Many modern payers prefer you use these instead: XE (Separate Encounter): Use this if the services occurred during totally different visits on the exact same day. XS (Separate Structure): Use this if you performed the therapy on a completely different anatomical site than the adjustment. This is the most common replacement for Modifier 59 in
What Happens If You Don’t Pay Your Medical Bills? A Step-by-Step Timeline
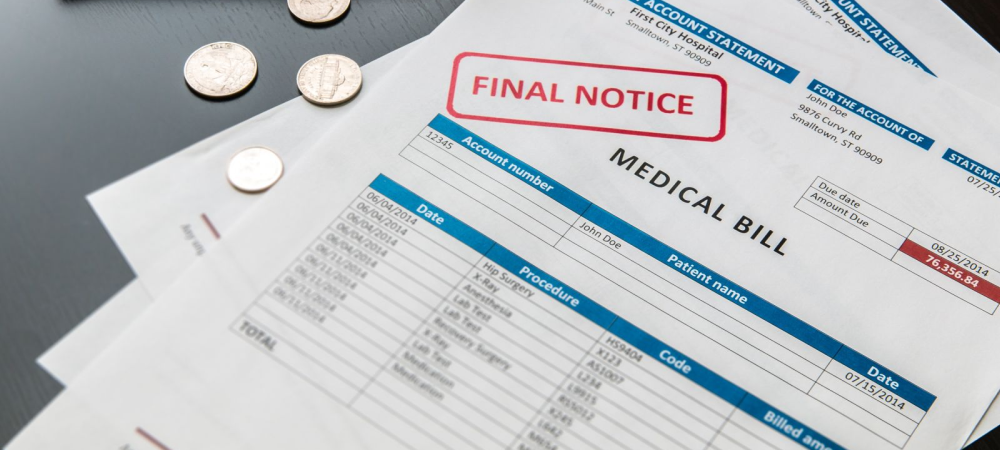
Receiving a massive medical invoice in the mail is highly stressful. When faced with a bill you simply cannot afford, the easiest reaction is to toss it in a drawer and hope it goes away. However, ignoring a medical bill does not make it disappear. While unpaid healthcare debts do not trigger immediate legal penalties, they set off a slow, escalating timeline of consequences. Understanding what happens if you don’t pay your medical bills helps you take control of a frightening situation. The collection process moves through specific phases, starting with gentle reminders and ending with potential credit damage or legal action. Fortunately, you have specific rights and opportunities to fix the problem at every stage of this timeline. Whether you are dealing with a simple clinic visit or a major hospital stay, knowing how the medical bill collections system works gives you the power to protect your finances. This guide breaks down exactly what to expect over the first year of an unpaid medical debt. The First 30 to 60 Days – The Initial Notice Phase When a healthcare provider sends your first invoice, the clock officially starts. During this early window, the hospital or clinic assumes that you simply forgot to pay or that you need time to organize your finances. The tone remains polite and strictly administrative. During the first 60 days, you will receive basic billing statements in the mail or via email. If you miss the first due date, a second reminder usually follows about a month later. Why Your Credit Score is Safe Early On One of the biggest fears patients have is that a missed deadline will ruin their credit immediately. During the first two months, your credit score is completely safe. Hospitals do not report late payments to credit bureaus directly. They keep the debt in-house while trying to collect the money themselves. The Best Time to Check for Errors This early phase is the perfect time to review the invoice closely. Billing departments make mistakes constantly. Take these actions to protect yourself: Request an Itemized Bill: Ask the provider to send a detailed list of every charge. You might find charges for medications you never received or procedures that never happened. Verify Insurance Processing: Ensure the clinic actually billed your health insurance correctly. Sometimes, a simple typing error on your policy number causes a claim to bounce back to you. Dispute Mistakes Fast: If you spot an error, call the billing office immediately. Placing the bill in dispute usually pauses the collection timeline while they investigate. Day 30 to 90 – Internal Escalation and Added Fees If two or three months pass without a payment, the provider changes their strategy. The polite reminders stop, and the notices become much firmer. The hospital or clinic billing department will now flag your account as seriously past due. Firmer Warnings and Extra Charges At this stage, the hospital wants to force a reaction. You might start receiving automated phone calls asking you to settle the balance. Additionally, providers may add late fees or internal interest charges to your original balance. These extra fees make the debt even harder to pay off, so ignoring the letters only increases your financial burden. Reaching Out for Payment Plans Even though the letters look intimidating, the provider still wants to work with you directly. They would much rather accept a small monthly payment than sell your account to a debt collector for pennies on the dollar. Most hospitals offer financial assistance programs. If you call their billing office, you can often negotiate a reasonable monthly payment plan. Many clinics also offer charity care programs that forgive the debt entirely if you can prove financial hardship. Do not let fear stop you from picking up the phone. Day 90 to 180 – The Shift to Medical Bill Collections The six-month mark is a major turning point for unpaid healthcare debt. Hospitals and doctors are not in the business of chasing down money forever. If an account sits unpaid for 90 to 180 days, the provider usually gives up on collecting it themselves. Third-Party Debt Collectors Take Over At this point, your account is sold or assigned to a third-party collection agency. This is when medical billing collections truly begin. Expect a major shift in communication style: Persistent Phone Calls: Debt collectors will call your home and cell phone frequently. Demand Letters: You will receive official collection letters demanding immediate payment. Debt Validation: Under federal law, you have the right to request a “debt validation letter” to prove the collector legally owns the debt and that the amount is accurate. The $500 Credit Reporting Rule For years, any unpaid medical bill could ruin your credit score instantly. Recently, consumer protection laws have changed dramatically to protect patients. Today, credit bureaus follow strict rules regarding healthcare debt. Unpaid accounts under $500 generally do not appear on credit reports at all. If your bill is $400 and goes to collections, it will not drop your credit score. For balances over $500, credit reporting rules typically provide a one-year grace period before the debt hits your credit report. This year-long window gives you ample time to negotiate a settlement or fix insurance errors before your financial reputation takes a hit. Beyond One Year – Legal Action and Credit Damage If a large medical bill remains completely unresolved after an entire year, the situation becomes highly serious. The protective grace periods expire, and the collection agencies deploy their heaviest tactics. When Collections Damage Your Credit Once the one-year grace period ends, unpaid balances over $500 are officially reported to the major credit bureaus (Equifax, Experian, and TransUnion). When a collection account appears on your credit report, it causes severe damage. A lowered credit score makes it incredibly difficult to secure a car loan, get approved for a mortgage, or even rent a new apartment. Fortunately, under new guidelines, if you eventually pay off that collection account, the credit bureaus will remove it from
Is Medical Billing And Coding Hard? A Realistic Look At The Learning Curve

When people look for a stable career in healthcare that does not require direct patient care, revenue cycle management often catches their eye. A common question quickly follows. Is medical billing and coding hard to learn? The short answer is that it takes real dedication. You are essentially learning a completely new language. Medical billers and coders act as the financial bridge between healthcare providers and insurance companies. To do this job well, you must study complex anatomy, memorize medical terms, and learn how to use strict rule books like ICD-10 and CPT codes. While it requires serious brainpower, it is absolutely manageable with the right study plan. Most certificate programs take four to eighteen months to complete. If you put in the hard work, you can pass the certification exams and start a steady, rewarding career in healthcare. In this guide, we give you a realistic look at the training process, the daily skills required, and the best ways to conquer the learning curve. This career sits at the intersection of many different types of billing in healthcare, from professional to institutional claims, which is part of why the learning curve covers so much ground. What Makes the Learning Curve Feel Difficult? Learning any new professional skill takes time and patience. When you ask if is billing and coding hard, the challenge usually comes from the sheer volume of information you must absorb. You are not just learning how to type numbers into a computer system. You are learning how to read detailed doctor notes and turn them into a flawless financial record. Mastering the Language of Medicine Before you can code a medical chart, you have to understand what the doctor actually did during the patient visit. This requires a strong foundation in human biology and medical phrasing. Greek and Latin Roots Most medical terms come from Greek and Latin word parts. You must learn the prefixes, root words, and suffixes that build these complex terms. For example, knowing that “osteo” means bone and “itis” means inflammation helps you easily understand that “osteoarthritis” is a bone and joint problem. This foundational knowledge helps you name body parts, identify diseases, and understand surgical cuts accurately. Anatomy and Physiology You also have to study human anatomy. To code a surgical procedure correctly, you have to know exactly where a specific organ is located and how it connects to other body systems. You will learn about the cardiovascular system, the nervous system, and the digestive tract in great detail. Working With Massive Coding Manuals Medical coders do not guess. They rely on strict, heavy rule books to find the exact codes needed for billing. ICD-10 for Diagnoses The ICD-10 manual contains codes for every illness, injury, and symptom known to medicine. If a patient comes in with a broken arm, you must find the exact code that describes which bone is broken and whether it is the left or right arm. CPT for Procedures The CPT manual lists the codes for the actual treatments and procedures the doctor performed. This includes everything from a routine checkup to a complex open-heart surgery. You must read the doctor’s notes carefully to pick the exact procedure code that matches the service provided, a skill that becomes even more specific once you compare it against something like this physician vs facility billing guide. HCPCS Level II for Supplies The HCPCS manual covers the extra items used during a medical visit. This includes codes for ambulance rides, prosthetic limbs, crutches, and specific injected drugs. Knowing when to use these supply codes ensures the doctor gets paid for the materials they used. Precision Matters Finding the right code involves checking multiple indexes and reading specific guidelines. Small errors lead to denied claims. If you code a left leg procedure on the right leg by mistake, the insurance company will reject the payment instantly. Precision is the most important skill you will develop. Some billing scenarios raise the precision bar even further, such as the simultaneous conditions covered in this incident-to billing rules guide. Computer Skills and Software Demands Today, healthcare runs entirely on computers. You need to use electronic health records and specialized billing software daily. You do not need to be a computer programmer, but you must feel comfortable switching between different digital screens. You will type data, attach medical records, and submit electronic claims to insurance portals. Being comfortable with basic keyboard shortcuts and digital folders will make your daily work much easier. Keeping Up With Yearly Rule Changes The learning never truly stops in this profession. Insurance rules and code sets update every year. The government adds new disease codes and removes outdated ones. You must keep learning new rules to maintain your credentials. Most certification boards require you to complete continuing education credits annually to prove your skills are current. If you enjoy learning new things, this constant evolution keeps the job interesting. Breaking Down the Study Time and Training Options The amount of time you spend in school directly affects how hard the learning curve feels. You can choose a fast path or a slower, more detailed path depending on your personal schedule. Program Lengths: Certificates vs Degrees Schools offer different paths depending on your career goals and your budget. You must decide how much time you can commit to studying each week. Certificate Programs (4 to 18 Months) Certificate programs are the most popular route. These programs focus strictly on the skills you need for the job. You skip the general education classes like history or literature. Depending on your pace, you can finish a certificate in four to twelve months. This is an excellent option if you want to enter the workforce quickly and start earning a paycheck. Associate Degrees (24 Months) An Associate degree typically takes about two years to finish. This path includes general education classes alongside your coding classes. A degree might give you an edge if you want to move into management roles or hospital
Medical Billing Company Near Me – How to Vet a Local vs. Remote Partner

Managing a successful healthcare practice takes exceptional focus and dedication to patient care. When your administrative staff spends hours fighting with insurance payers, your entire clinic suffers. Outsourcing your revenue cycle management is a smart operational decision. However, finding the right administrative partner involves asking the right questions. Practice owners often begin their search by looking for a medical billing company near me. They want a partner they can trust with their financial data. Choosing a revenue cycle partner requires balancing proximity and regional expertise against remote scalability and cost. Some clinics prefer local companies because they offer face-to-face accountability. Other clinics choose remote teams that use advanced cloud automation. Evaluating these options properly protects your practice from unpaid claims and strict regulatory fines. This detailed guide explores how to vet local and remote vendors effectively. At YTC Healthcare, we provide a reliable medical billing service tailored to your exact needs. Read on to discover the exact metrics and contract details you must review before signing a new agreement. Evaluating the Core Differences Between Local and Remote Vendors The healthcare industry offers many different outsourced solutions. When you start reviewing medical billing companies near me, you will notice a stark contrast between local agencies and large remote operations. Both models present unique operational strengths. Selecting the right fit depends entirely on your clinic size, your daily workflow preferences, and your regional insurance environment. The Advantages of Hiring a Local Medical Billing Service Working with a local vendor provides a sense of comfort for many practice owners. Having a physical office nearby changes how you interact with your billing team. Face-to-Face Communication and Accountability A local partner excels at direct communication. If a major billing issue arises, you can schedule an in-person meeting to resolve the problem quickly. This high-touch environment builds deep trust between your clinic manager and the billing team. When your billing representatives live in the same city, they understand the local healthcare landscape personally. They are highly accountable because they operate within your immediate community. Deep Expertise in Regional Compliance Rules Local billing firms possess incredible knowledge of regional payer rules. For example, if you practice in Ontario, your billers must understand the strict nuances of the Ontario Health Insurance Plan (OHIP). Ontario’s broader healthcare landscape shapes this too, a dynamic covered in this piece on why care homes need staffing agencies. A local team understands these specific regional nuances perfectly: Provincial Health Ministries: Managing specific claim submission portals for government insurance plans. Workers’ Compensation: Processing claims accurately through regional boards like WSIB. Local Private Insurers: Knowing the exact billing modifiers preferred by local commercial health networks. The Benefits of Choosing a Remote Billing Partner While local agencies offer great regional knowledge, remote teams provide massive scale and efficiency. Remote billing companies manage claims for clinics across the entire country. Cloud Automation and Advanced Technology Integration Remote teams invest heavily in top-tier technology. They use cloud-based software to automate claim scrubbing, payment posting, and demographic data entry. This advanced technology speeds up the entire revenue cycle. Since they operate remotely, they integrate seamlessly with your existing Electronic Health Record (EHR) system through secure digital portals. This kind of automation doesn’t eliminate the underlying skill requirement, which is part of why is medical billing coding hard remains a common question even as technology advances. Scalability and Flexible Cost Structures Remote vendors often offer highly competitive pricing models. Because they operate at a massive scale, they can process a higher volume of claims efficiently. Understanding typical compensation for the billing and coding roles behind these cost structures is covered in this medical coder salary guide. Their cost structures usually feature: Variable Volume Tiers: You pay less per claim as your clinic grows and your patient volume increases. Lower Overhead Passing: Remote teams operate without expensive downtown office spaces, passing those savings directly to your clinic. Cross-Trained Staffing: If one biller takes a vacation, another trained expert steps in immediately without pausing your cash flow. Quick Comparison Table: Local vs. Remote Partners Review this simple comparison matrix to see how these two models stack up against each other. Feature Area Local Medical Billing Partner Remote Medical Billing Partner Communication Style In-person meetings and high-touch local support. Virtual channels via email, phone, and secure portals. Regional Rule Knowledge Exceptional expertise in local and provincial nuances. Varies by vendor; you must verify their specific jurisdiction experience. Software Technology Ranges from traditional desk software to modern systems. Typically utilizes highly automated, cloud-based infrastructure. Standard Cost Structure Often uses fixed rates or slightly higher percentage fees. Frequently uses competitive volume tiers and variable percentage rates. Key Vetting Strategies for Any Medical Billing Partner Whether you choose a local agency or a remote powerhouse, you must conduct a thorough background check. Handing over your revenue cycle is a massive financial risk. You must vet every potential partner using a strict set of performance criteria. Reviewing Clean-Claim Metrics and Submission Rates The speed of your cash flow depends entirely on claim accuracy. An insurance company will reject a claim instantly if it contains a simple spelling error or a missing billing modifier. The Importance of High First-Pass Acceptance You must look for a first-pass submission rate consistently above 90 percent. This metric shows how many claims the billing company gets paid on the very first try. A high first-pass rate proves that the vendor scrubs their claims carefully before hitting the submit button. Ask the vendor to show you actual reports demonstrating their clean-claim success over the past six months, and confirm they distinguish between claim types the way this physician vs facility billing guide does. Inspecting the Claim Denial Management Workflow Even with excellent coding, insurance companies will deny some claims. How a billing company handles these rejections determines your final monthly revenue. Tracking, Appealing, and Reporting Rejected Claims A weak billing company will process the easy claims and ignore the difficult denials. You must ask how they track, appeal, and report rejected claims.
How to Choose Medical Billing Companies – A Practice Owner’s Checklist

Running a medical practice requires balancing high-quality patient care with strict financial management. Finding the right administrative support is a critical step for independent practitioners. While you focus on health outcomes, your back-office operations must handle a complex web of insurance codes and compliance rules. Choosing to outsource your revenue cycle is smart, but selecting the right partner determines your financial success. Many practices start that search by partnering with medical billing services built specifically around this kind of evaluation. With countless options available, identifying reliable medical billing companies takes careful evaluation. You need a partner who understands regional billing nuances, prioritizes software transparency, and minimizes claim rejections. A weak billing firm can cost you thousands in missed revenue, while a strong partner acts as a seamless extension of your clinic. This detailed checklist helps practice owners cut through the marketing noise. We explore exactly what to look for regarding technology, compliance, and pricing structures so you can confidently select the best medical billing company near me or abroad. Evaluating Core Performance and Technological Capabilities When you hand over your revenue cycle to an external medical billing firm, you are trusting them with the financial lifeblood of your clinic. The technology they use and the operational standards they maintain dictate how quickly you get paid. A modern billing partner must offer more than just data entry. They need advanced software capabilities and a proven track record of fighting for your revenue every single day. Claim Accuracy and First-Pass Denial Rates The most important metric any billing company can provide is their first-pass denial rate. This number indicates the percentage of claims that are rejected by insurance payers on the very first submission attempt. Why the First Pass Matters If a claim is rejected, it requires manual review and resubmission. This delays your cash flow and increases administrative costs. You should always target a partner aiming for extremely low rejection numbers. A highly competent billing service scrubs every claim through automated error-checking software before hitting the submit button. Ask potential vendors to provide their current average first-pass acceptance rates and compare them against national averages for your specific medical specialty. Coding accuracy sits at the center of this metric, which is part of why so many billers themselves ask is medical billing coding hard when weighing the learning curve involved. Software Transparency and Real-Time Dashboards Many older billing agencies operate like a closed box. You send them your patient encounters, and a month later, they send you a check and a confusing paper report. This lack of transparency is unacceptable for a modern clinic. You must pick a system offering real-time digital dashboards. A transparent software setup allows practice owners to log in at any time to view outstanding accounts receivable, track pending appeals, and review daily collection totals. Having instant access to your financial data ensures that you never lose sight of your business performance. Navigating Canadian Provincial Billing Rules For Canadian practitioners operating under provincial insurance systems like OHIP (Ontario Health Insurance Plan), the billing rules differ significantly from private commercial insurance models. Your chosen partner must possess deep regional expertise. Essential Provincial Billing Features When evaluating a vendor for Canadian operations, verify that their software supports these critical functions: Electronic Batch Submissions: The ability to send hundreds of claims securely in a single digital batch to the Ministry of Health. Error Reconciliation: Automated tools that flag specific OHIP rejection codes and allow billers to correct and resubmit them instantly. Real-Time Fee Schedule Updates: The system must verify that regional code and dollar value changes update automatically as the government releases new payment guidelines. For new clinics, reviewing guidance from The Ontario Medical Association on starting a practice provides excellent baseline knowledge. Additionally, review resources like Royal Bank for essential billing software capabilities and financial integration tips. Canadian practices researching this space often run into related staffing questions too, a topic covered in this piece on why care homes need staffing agencies. Analyzing Business Practices and Compliance Standards Beyond software and claim submission speeds, the business structure of your chosen billing partner heavily impacts your clinic. You must ensure they operate ethically, understand your specific medical niche, and charge a fair price for their labor. If a company fails in these areas, even the best software will not save your bottom line. Matching Specialty Fit and Credentialed Staff Medical coding is not a universal language. The treatment codes used by a pediatric clinic look completely different from the surgical codes used by an orthopedic specialist, and the same holds true between claim types, as shown in this physician vs facility billing guide. Confirm that the billing company understands your specific medical domain’s coding nuances. Ask to speak with the account manager who will handle your file. Ensure their internal coders hold active, recognized certifications from professional bodies like the AAPC (American Academy of Professional Coders) or AHIMA (American Health Information Management Association). Certified coders reduce errors and protect your clinic from government compliance audits, and understanding typical compensation for that level of expertise is covered in this medical coder salary guide. Understanding Pricing Structures and Hidden Costs Pricing models vary wildly across the billing industry. Most agencies charge a percentage of the total revenue they collect successfully on your behalf. While comparing fees is important, you must look closely at what that fee actually includes. Avoid ultra-low percentage fees under 4 percent. These budget rates often lead to cut corners, underpaid staff, and missed revenue. A cheap billing company might easily process the simple claims that pay quickly but ignore the difficult denied claims that require time-consuming phone calls to resolve. Paying a slightly higher percentage to a dedicated firm often yields a much higher total revenue collection. Support Evaluation and Local Resources Customer support separates a decent vendor from an exceptional medical billing company. If you have an urgent question about a massive insurance denial, you need a partner who answers the phone promptly. Consult professional resources